You are revising around a full-time supervised foundation training placement. You are dispensing, counselling patients, completing competency sign-offs, and building a portfolio. The revision plan that assumes 4-hour evening study sessions will collapse by week 2 — because you will be too tired, and the resentment of an unrealistic plan kills motivation faster than the exam content itself.
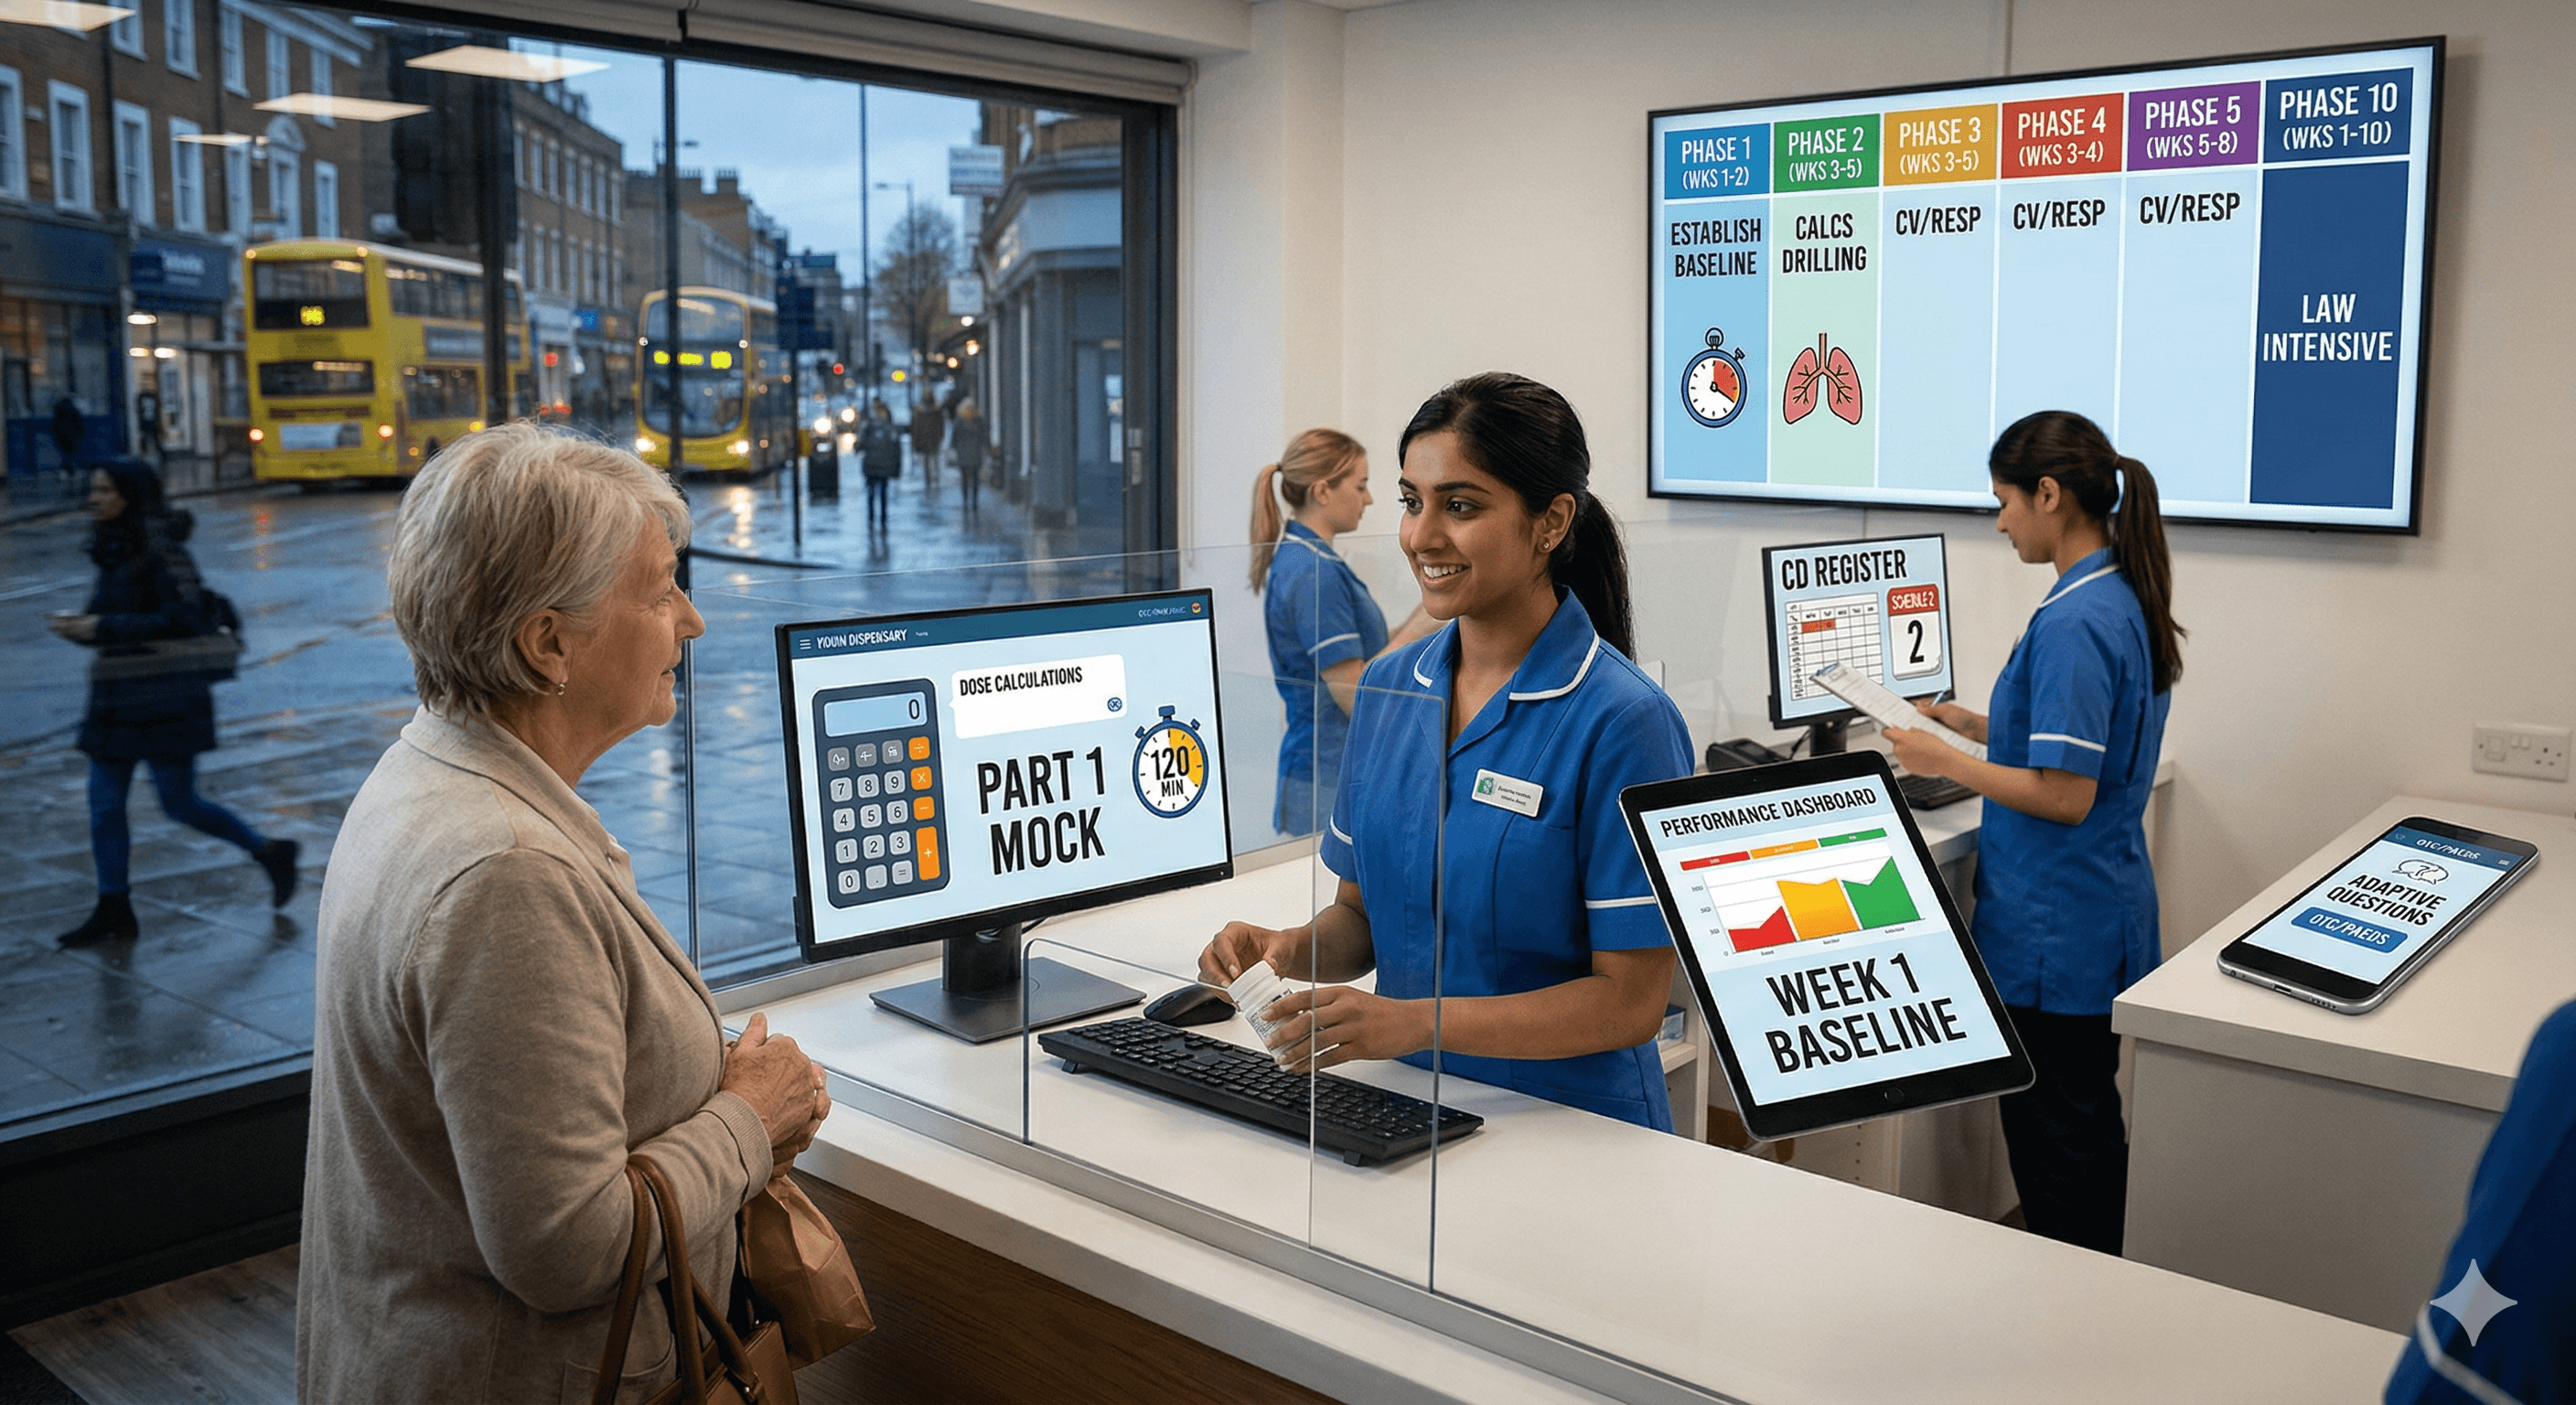
This plan assumes 1-2 hours per day on 6 days each week. It frontloads calculations, then builds clinical and law knowledge according to the official CRA framework and the learner’s performance data. Each phase names the kind of resource it needs, because structured teaching, source verification and timed application are different tasks.
Phase 1 — Diagnostic and Calculation Foundation (Weeks 1-2)
Week 1: Establish Your Baseline
Monday: Download the CRA framework from the GPhC website. Read the indicative assessment topics and therapeutic area weightings. This is your revision blueprint — everything else is guided by this document. (30 minutes)
Tuesday-Wednesday: Complete the GPhC official example questions on the Surpass platform. Get familiar with the interface — the on-screen calculator, the question navigation, the EMQ format. Exam-day surprises cost time. Eliminate them now. (45 minutes each day)
Thursday-Saturday: Complete a 50-question mixed diagnostic on iatroX. Do not revise beforehand — this is a baseline, not a test. The performance dashboard will show your starting proficiency across all CRA content areas. Write down your 3 weakest therapeutic areas and your 2 weakest calculation types. These are your priority targets for the next 7 weeks. (60 minutes total across 3 days)
Week 2: Calculation Types — Isolation Drilling
Monday-Tuesday: Dose calculations and unit conversions. 20 timed questions per day on iatroX. Use your actual exam calculator. Every question timed — 3 minutes maximum. (45 minutes each day)
Wednesday-Thursday: IV infusion rates and drip rates. Same format. Focus on the unit conversion step — mcg to mg, minutes to hours. This is where the errors happen. (45 minutes each day)
Friday-Saturday: Displacement values and concentration expressions. These are the two types candidates under-prepare most — drill them specifically now rather than discovering the gap in week 7. (45 minutes each day)
Resource note: For calculations, you need practice, not teaching. If you do not understand the method for a specific type, watch a Pharmacy Masterclass or Pre-Reg Shortcuts calculation tutorial for that type — then immediately drill it on iatroX. Teaching without practice does not transfer. Practice without understanding does not stick. The sequence matters: understand the method → drill under timed conditions → repeat.
Phase 2 — Systematic Part 2 Clinical Content (Weeks 3-5)
Week 3: Cardiovascular and Respiratory
Daily (60 minutes): Build the cardiovascular and respiratory domains in the official CRA framework using structured notes or taught sessions. Cover hypertension, heart failure, atrial fibrillation, anticoagulation and lipid management with applicable NICE guidance; then cover asthma and COPD with current NICE/BTS/SIGN and local guidance. Check relevant SmPCs on eMC for product-specific licensed information, then finish with applied questions.
Daily (30 minutes): 15 adaptive iatroX questions on cardiovascular and respiratory topics. The adaptive engine will concentrate on whichever sub-topics within these chapters you get wrong.
Week 4: CNS, Endocrine, Infection
Daily (60 minutes): CNS: depression (NICE NG222 — stepped care, SSRI selection, monitoring), epilepsy (NICE NG217 — first-line by seizure type, drug interactions, pregnancy), Parkinson's (NICE NG71), pain management (WHO ladder, opioid equivalence, adjuvants). Endocrine: diabetes type 1 and 2 (NICE NG28 — metformin → SGLT2i → GLP-1 sequencing; insulin types and monitoring). Infection: antibiotic stewardship, NICE community infection guidelines, high-risk infections.
Daily (30 minutes): 15 adaptive iatroX questions on CNS, endocrine, and infection.
Week 5: GI, Renal, Remaining Systems
Daily (60 minutes): Cover gastrointestinal disease, renal impairment, blood and nutrition, genito-urinary medicine and the immune system according to the official CRA framework. Use applicable NICE guidance for management, relevant SmPCs on eMC for product-specific information, and timed questions to practise application rather than passive recognition.
Daily (30 minutes): 15 adaptive iatroX questions across remaining systems.
Resource note: Structured teaching and notes are most useful while building knowledge in weeks 3-5. From week 6, shift towards timed retrieval, calculations and applied decision-making. Change the tool when the learning task changes.
Phase 3 — Law, Ethics, and Under-Revised Areas (Weeks 6-7)
Week 6: Pharmacy Law Intensive
Daily (60 minutes): This is the domain candidates consistently underperform on — and it carries predictable marks. Cover: Misuse of Drugs Act — schedules 2-5, CD prescription requirements, CD register rules, destruction procedures. Human Medicines Regulations — prescription validity, repeat prescriptions. Responsible Pharmacist Regulations — absence provisions, RP record. Emergency supply — patient-request vs prescriber-request (the most commonly confused distinction). GPhC Standards for Pharmacy Professionals — all 9 standards.
Daily (30 minutes): 15 iatroX law and governance questions in adaptive mode. The engine will identify which law topics you confuse and concentrate practice there.
Week 7: OTC, Minor Ailments, Paediatrics, Remaining Gaps
Daily (60 minutes): OTC counselling scenarios, Pharmacy First pathways, minor ailments management, paediatric dosing (current UK paediatric medicines information — weight-based doses and maximum dose checking), and pregnancy/breastfeeding prescribing considerations. These are the areas most candidates under-revise because they feel less "clinical" — but they carry reliable marks.
Daily (30 minutes): 15 iatroX adaptive questions — mixed topics, including paediatrics and OTC scenarios.
Dashboard checkpoint: Review your iatroX performance dashboard at the end of week 7. Any CRA content area still showing red is your priority for week 8. If everything is amber or green, week 8 is consolidation. If one or two areas are red, week 8 is targeted rescue.
Phase 4 — Mock Conditions and Consolidation (Week 8)
Week 8: Exam Simulation
Monday: Full Part 1 mock — 40 calculations, 120 minutes, timed, using your exam calculator. Do not pause. Do not look up methods. Simulate real conditions. Score it. Identify which calculation types you still lose marks on.
Tuesday: Full Part 2 mock — 120 questions, 150 minutes, timed. Score it by domain (therapeutics vs law vs calculations embedded in clinical scenarios).
Wednesday-Thursday: Targeted drilling on the weakest areas from both mocks using iatroX adaptive mode. This is where the adaptive engine earns its value — it already knows your weak areas and will serve exactly the questions you need.
Friday: Light review. CD schedules. Paediatric dosing. The two topics the Board of Assessors flags most consistently. Read the Board of Assessors feedback from the most recent sitting — it tells you exactly what current candidates get wrong.
Saturday: Rest. No revision. Sleep well. The exam is Monday or Tuesday.
Which Resources Serve Which Phase
This plan is not anti-PharmX, anti-Coditioning, or anti-Focus Pre-Reg. It is pro-sequencing — using the right tool at the right time.
Weeks 1-5 (knowledge building): Use structured notes, taught sessions or another systematic resource to cover the official CRA domains. Build enough understanding to explain the clinical and legal reasoning, then move progressively into timed application; do not treat any commercial resource’s chapter order as the assessment blueprint.
Weeks 2-8 (knowledge testing): This is where iatroX earns its value. The adaptive engine converts passive knowledge into active retrieval fluency — the ability to produce the correct answer under time pressure, not just recognise it when you see it. The performance dashboard tracks your progress by CRA content area and identifies which topics need more work each week.
Weeks 6-7 (law and governance): This is where most candidates under-invest. Pharmacy law does not map neatly to MPharm training or daily dispensing. It requires dedicated study time — and adaptive question practice that drills the specific regulatory scenarios the exam tests (CD prescription validity, emergency supply conditions, RP absence provisions).
Throughout (source verification): When a question explanation raises a “what exactly does NICE say?” query, Ask iatroX can retrieve cited guidance. Open the cited source, check its date and applicability, and record any relevant local or assessment-specific context.
Combining structured notes, retrieval practice and source verification gives each tool a clear role: notes organise knowledge, questions expose gaps, and cited source material helps resolve them. Candidates should choose a mix that fits their own baseline, schedule and assessment needs.
The Three Most Common Ways This Plan Derails (and How to Prevent Them)
Derailment 1: Skipping week 1. Candidates who skip the baseline diagnostic and jump straight into content revision are revising blind. They do not know which areas need the most work. They spend week 3 on cardiovascular (which they are already strong in from MPharm) instead of endocrine (which they are weak in but do not realise). The week 1 diagnostic on iatroX takes 50 questions and one hour. It saves you weeks of misdirected effort. Do not skip it.
Derailment 2: Spending too long on calculations. Calculations are the most drillable section — and drilling feels productive, because you can see immediate improvement. Some candidates spend 4 weeks on calculations and run out of time for Part 2 clinical content. The plan allocates 2 weeks to calculations (with ongoing maintenance in mixed sessions). If your calculation proficiency is amber or green on the iatroX dashboard by end of week 3, move on. Do not over-invest in your strongest area at the expense of your weakest.
Derailment 3: Abandoning the plan in week 6. By week 6, exam anxiety peaks. Candidates abandon the structured plan and switch to panicked, random question practice — doing 100 mixed questions per day with no targeting, no review of wrong answers, and no strategic focus. This feels productive (high question volume) but is not (no targeting, no learning from errors). The plan exists to prevent this. Trust the dashboard. Target the red areas. Resist the urge to do more at the expense of doing better.
Why This Plan Works
The plan separates knowledge building (PharmX slides, Focus Pre-Reg sessions, reviewing official medicines references) from knowledge testing (iatroX adaptive questions). Most candidates do not make this distinction — they read and re-read, or they do questions without building the knowledge first. The sequence matters: build → test → verify → consolidate.
The plan embeds iatroX at every phase — not as an add-on, but as the adaptive engine that guides which topics receive the most attention. The performance dashboard replaces guesswork with data. And the mobile app means the 30-minute daily question sessions can happen on the bus, in the dispensary, or before bed — wherever you have your phone.
Set your week-one baseline at iatrox.com/quiz-landing?exam=uk-gphc.